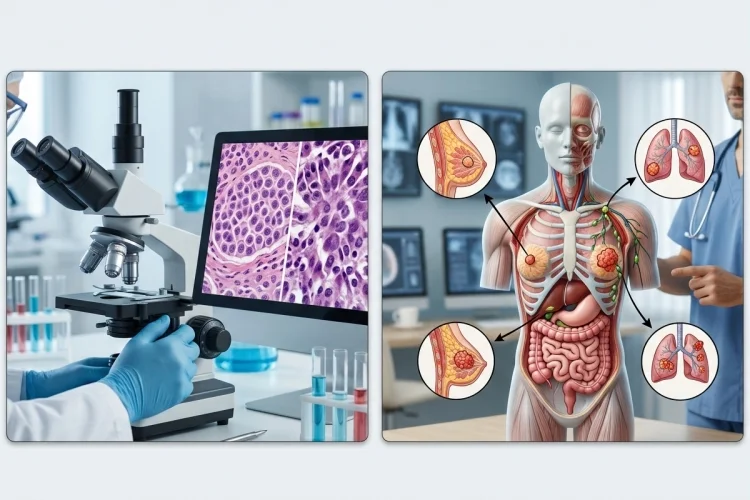
Imagine two patients diagnosed with the same type of cancer. One has a small tumour whose cells look extremely abnormal under the microscope. The other has a larger tumour made of cells that still resemble the normal tissue they came from.
Which cancer is more serious?
The answer is not always obvious because cancer has several different ways of describing severity. Two of the most important are tumour grade and cancer stage, and they describe very different aspects of the disease.
Tumour grade mainly tells us what the cancer cells look like and how biologically aggressive they are likely to behave. Cancer stage tells us how much cancer is present and how far it has spread through the body.
The National Cancer Institute specifically distinguishes grade from stage: grade is based on microscopic appearance, while stage reflects tumour extent and spread.
Understanding how tumour grade differs from cancer stage in pathology makes pathology reports much easier to read and helps explain how doctors estimate prognosis and plan treatment.
What Is Tumour Grade?
Tumour grade describes how abnormal cancer cells and tissues appear when examined by a pathologist under a microscope.
One of the main concepts behind grading is differentiation.
A well-differentiated cancer still resembles the normal tissue from which it developed. The cells may maintain some of the original tissue architecture and specialized characteristics.
A poorly differentiated tumour looks much less like its tissue of origin. Cells may have irregular nuclei, abnormal architecture, increased mitotic activity, and other features suggesting more aggressive biological behaviour.
In general, lower-grade tumours tend to behave less aggressively, while higher-grade cancers tend to grow and spread more rapidly. However, grading systems vary between cancer types and cannot be interpreted using one universal rule.
The grade is therefore answering a microscopic question:
“How abnormal and aggressive does this cancer look?”
How Pathologists Determine Tumour Grade
Pathologists determine grade by examining tissue obtained from a biopsy or surgical specimen.
The exact criteria depend on the tumour. There is no single grading system that works for every cancer.
For many tumours, the pathologist evaluates features such as cellular differentiation, nuclear abnormalities, tissue architecture, and the number of mitotic figures.
Some cancers use specialized scoring systems that combine several microscopic features before assigning the final grade.
A simplified system might describe tumours as:
Low grade: cells remain relatively similar to normal tissue.
Intermediate grade: cells show a greater degree of abnormality.
High grade: cells appear poorly differentiated or highly abnormal and often demonstrate more aggressive characteristics.
Cancer-specific systems can be more detailed. Breast cancer, for example, uses a histologic grading system based on features such as tubule formation, nuclear appearance, and mitotic activity.
The important lesson is that grade comes primarily from microscopic pathology.
A CT scan can show where a tumour is located, but it cannot replace the pathologist’s assessment of cellular differentiation.
What Is Cancer Stage?
If grade describes what cancer looks like, stage describes where it is and how far it has gone.
The National Cancer Institute defines cancer stage as the extent of cancer in the body, including characteristics such as the size of the primary tumour and whether the disease has spread.
Stage therefore focuses primarily on anatomy rather than microscopic appearance.
Questions involved in staging include:
How large is the primary tumour?
Has it invaded nearby structures?
Has cancer reached regional lymph nodes?
Has it spread to distant organs?
Many cancers are eventually grouped into stages ranging from stage I to stage IV, although the exact definitions vary by tumour type. Lower stages generally represent more localized disease, while higher stages indicate more extensive spread.
Some cancers also have stage 0, usually referring to certain forms of carcinoma in situ.
So the key staging question is:
“How far has the cancer spread?”
How the TNM System Describes Cancer Spread
One of the most widely used methods of cancer staging is the TNM system.
TNM separates the anatomical extent of cancer into three major components.
1. T: Primary Tumour
T describes the primary tumour. Depending on the cancer type, this can reflect tumour size, depth of invasion, or extension into nearby tissues.
A higher T category generally represents greater local tumour involvement, although specific definitions differ between organs.
2. N: Regional Lymph Nodes
N describes whether cancer has reached nearby or regional lymph nodes and, depending on the cancer, factors such as the number or location of involved nodes.
Lymph-node involvement is important because lymphatic channels provide one route through which malignant cells can spread away from the primary site.
3. M: Distant Metastasis
M describes whether cancer has spread to distant parts of the body.
The NCI summarizes the system simply: T refers to the primary tumour and nearby tissue involvement, N to regional lymph nodes, and M to distant metastasis.
These categories can then be combined with cancer-specific rules to assign an overall stage.
Grade and Stage Measure Different Things
The easiest way to remember the difference is:
Grade = what the cancer looks like
Stage = where the cancer has gone
That distinction means a high-grade cancer is not automatically a high-stage cancer.
For example, imagine a small malignant tumour discovered early. Under the microscope, the cells are poorly differentiated and highly abnormal. The tumour might therefore receive a high grade.
However, imaging and surgery may show that it remains confined to its original organ without regional lymph-node or distant spread.
It could be high grade but relatively low stage.
Now consider the opposite situation.
A tumour may contain relatively well-differentiated cancer cells, giving it a lower histologic grade, but the disease may already have spread to distant organs.
That cancer could be lower grade but advanced stage.
This difference is fundamental because grade and stage provide complementary information rather than two versions of the same measurement.
Clinical Stage and Pathological Stage Are Also Different
Another source of confusion is the distinction between clinical staging and pathological staging.
Clinical stage is generally estimated before definitive surgery using information from the physical examination, imaging studies, biopsies, endoscopic procedures, and other diagnostic tests.
Pathological staging usually becomes possible when tissue removed during surgery can be examined directly.
A pathologist may determine how deeply the tumour invaded surrounding structures and whether sampled regional lymph nodes contain metastatic cells.
NCI’s SEER training materials note that pathological stage is generally assigned after resection and analysis of the primary tumour, with regional lymph-node evaluation also important for many cancers.
This distinction explains why a patient’s stage can occasionally become more precise after surgery.
Imaging might suggest that lymph nodes are normal, for example, while microscopic examination later reveals a small metastatic deposit.
Where Grade and Stage Appear in the Pathology Report
A surgical pathology report can contain several separate pieces of information that should not be confused with one another.
The report may identify the histologic type, describing what type of cancer is present.
It may then provide the tumour grade, reflecting microscopic differentiation or another cancer-specific grading system.
Other sections can describe tumour size, depth of invasion, surgical margins, lymphovascular invasion, lymph-node involvement, biomarkers, and other features.
For an appropriate surgical specimen, these findings may also contribute to pathological staging. NCI notes that surgical pathology reports can include tumour grade, lymph-node status, margin status, and stage-related information.
The College of American Pathologists also publishes standardized cancer protocols containing essential reporting elements for malignant tumours.
So when reading a pathology report, do not expect one number to summarize the entire cancer.
Why Tumour Grade Matters for Prognosis
Tumour grade provides clues about the biological behaviour of a cancer.
Cells in a high-grade tumour generally show greater departure from normal differentiation and often demonstrate features associated with faster growth.
For this reason, grade can contribute to estimates of prognosis and may influence treatment decisions.
However, the importance of grade varies dramatically between cancer types.
Some cancers have well-established grading systems that strongly influence clinical management. Others rely more heavily on stage, molecular characteristics, biomarkers, or combinations of several factors.
A prostate cancer, breast cancer, brain tumour, sarcoma, and lymphoma should therefore not be expected to use identical grading rules.
This is why medical learners should avoid treating “grade 3” as though it means exactly the same thing in every malignancy.
Always interpret grade according to the specific tumour type and grading system being used.
Why Cancer Stage Matters So Much
Stage describes the anatomical burden and spread of disease, making it one of the most important pieces of information in cancer care.
A localized tumour may be potentially removable with surgery. Regional lymph-node involvement may require a broader treatment strategy. Distant metastatic disease can change both the goals and selection of therapy.
NCI notes that staging helps clinicians understand the seriousness of cancer, estimate prognosis, identify potential treatment approaches, and determine whether clinical trials may be appropriate.
Stage also allows doctors and researchers to compare groups of patients with similar extents of disease.
But stage should still not be viewed in isolation.
Modern cancer management can also depend on histologic subtype, tumour grade, molecular mutations, receptor status, patient health, treatment response, and many other disease-specific factors.
Cancer prognosis is increasingly understood through a combination of anatomy and biology.
Grade and Stage Can Work Together
The most useful approach is not asking whether grade or stage is “more important.”
They answer different questions.
Imagine a pathology report describing a cancer as high grade but localized. The stage suggests that the tumour has not travelled far, while the grade warns that its cellular biology may be aggressive.
Another cancer might be low grade but metastatic. Its cells may appear relatively differentiated, yet its anatomical spread shows that the disease has already established itself elsewhere.
In some cancer staging systems, biological factors such as tumour grade are actually incorporated into the final prognostic stage.
The American Cancer Society notes that, for some cancers, grade and other tumour-specific characteristics can contribute to stage grouping in addition to TNM information.
So although the concepts are different, they can ultimately work together to provide a more complete picture.
A Simple Way to Remember Grade vs Stage
For medical learners, one short phrase solves most of the confusion:
Grade = Face. Stage = Place.
Grade looks at the face of the cancer: What do the cells look like under the microscope? How differentiated or abnormal are they?
Stage looks at the place of the cancer: Where is the primary tumour? How far has it invaded? Are lymph nodes involved? Has it metastasized?
You can expand that into a practical sequence:
Biopsy → Identify tumour type → Determine grade → Assess tumour extent → Evaluate nodes and metastasis → Assign stage → Integrate everything for prognosis and treatment
Once you separate microscopic biology from anatomical extent, pathology reports become far easier to understand.
Tumour grade differs from cancer stage because the two measurements describe different dimensions of malignancy.
Grade is primarily a microscopic assessment of how abnormal or differentiated cancer cells appear and can provide clues about their likely biological aggressiveness.
Stage describes the anatomical extent of disease, including the primary tumour, regional lymph-node involvement, and distant metastasis.
A tumour can therefore be high grade but low stage-or relatively low grade but advanced stage.
For medical learners, remember the simple rule: grade describes appearance and behaviour; stage describes extent and spread.
When reading your next cancer pathology report, identify the tumour type, grade, T category, lymph-node status, and metastasis separately. Combining those pieces will give you a much clearer picture than any single number alone.