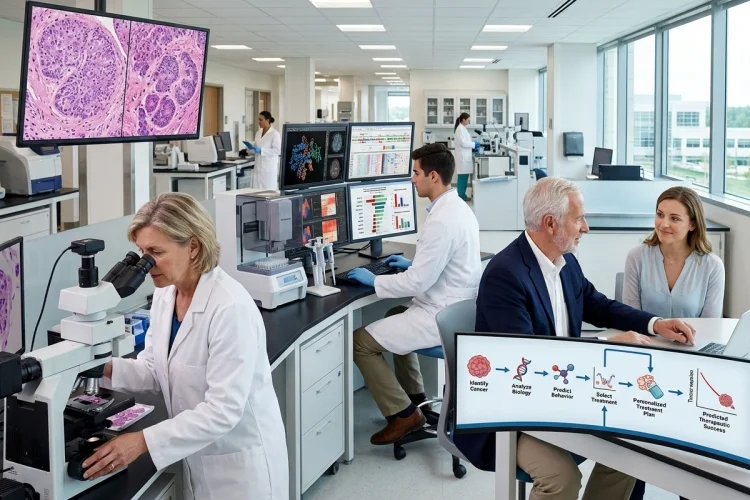
Two patients can have cancers that arise in the same organ and look similar under a microscope, yet their tumors may behave very differently.
One might respond extremely well to a particular targeted drug, while the other receives little benefit from the same treatment.
The difference may lie in cancer biomarkers.
A biomarker is a measurable gene, protein, molecule, or other biological characteristic that provides useful information about a cancer.
Biomarker testing can help identify tumor type, estimate prognosis, predict whether certain therapies are likely to work, monitor response, and sometimes detect recurrent disease.
Understanding how cancer biomarkers guide diagnosis and treatment is increasingly important for medical learners because modern oncology combines traditional pathology with molecular information.
A useful way to think about biomarkers is:
Identify the cancer → understand its biology → predict behavior → select treatment → monitor the response
That approach is one of the foundations of precision medicine, where therapy is increasingly matched to the biological characteristics of an individual tumor.
What Is a Cancer Biomarker?
A cancer biomarker is a biological feature that provides information about a tumor or its behavior.
Biomarkers can include proteins expressed on cancer cells, mutations in DNA, gene rearrangements, patterns of gene expression, or substances released into blood or other body fluids.
NCI notes that tumor markers may provide information about how aggressive a cancer is, whether targeted therapy may work, or whether the disease is responding to treatment.
Some biomarkers are detected directly in biopsy tissue. Others can be measured in blood, urine, bone marrow, or other specimens.
One important distinction is that somatic tumor biomarker testing is not the same as inherited genetic testing. Tumor testing usually looks for changes acquired by cancer cells, while germline testing looks for inherited variants present from birth.
For students, the word “biomarker” therefore covers a wide range of biological clues rather than one specific laboratory test.
Diagnostic Biomarkers Help Identify What the Tumor Is
Before deciding how to treat a cancer, the medical team first needs to know exactly what type of tumor is present.
Traditional pathology starts with morphology. A pathologist examines the biopsy and evaluates cell shape, tissue architecture, differentiation, and other microscopic features.
Sometimes morphology alone gives a clear diagnosis. In more difficult cases, immunohistochemistry and molecular testing provide additional clues.
Immunohistochemistry uses antibodies to detect specific proteins in tissue. Different cancers produce different patterns of protein expression, allowing pathologists to narrow the possible tissue of origin or distinguish tumors that look similar microscopically.
Molecular tests can further identify defining genetic alterations and are increasingly useful when tumors are difficult to classify.
A biomarker can therefore function like an identification badge.
Instead of simply saying, “These cells look malignant,” pathology can increasingly ask, “What biological identity do these malignant cells carry?”
Prognostic Biomarkers Tell Us About Likely Behavior
A prognostic biomarker provides information about how a cancer is likely to behave, regardless of a particular treatment.
For example, some biomarkers are associated with faster proliferation, greater likelihood of recurrence, or more aggressive tumor biology. NCI notes that tumor markers may contribute information about prognosis as well as cancer type and stage.
One familiar example is Ki-67, a protein associated with actively dividing cells.
In breast cancer, a higher proportion of Ki-67-positive tumor cells indicates greater proliferative activity. The result may contribute information about tumor behavior and, in selected settings, treatment response.
However, prognosis is rarely determined by one biomarker alone.
Tumor stage, histologic grade, molecular subtype, patient health, treatment response, and many other variables need to be considered together.
Think of a prognostic biomarker as answering:
“What does this tumor’s biology suggest about how it may behave?”
Predictive Biomarkers Help Choose Therapy
A predictive biomarker answers a different question:
“Is this cancer likely to respond to a particular treatment?”
This is one of the most powerful applications of biomarkers in modern oncology.
Certain treatments only work effectively when cancer cells contain a specific molecular target. NCI notes that some targeted therapies and immunotherapies depend on the presence of particular biomarkers.
EGFR Mutations in Lung Cancer
Some non-small cell lung cancers contain activating alterations in the EGFR gene.
When an actionable EGFR mutation is detected, therapies designed to inhibit abnormal EGFR signaling may become treatment options.
FDA-authorized companion diagnostic tests are available to identify specific EGFR alterations associated with approved targeted treatments in non-small cell lung cancer.
The logic is straightforward:
EGFR alteration detected → abnormal pathway identified → EGFR-targeted treatment may be considered
Without the biomarker, using that specific therapy may provide substantially less benefit.
This is precision oncology in its clearest form.
Breast Cancer Shows How Several Biomarkers Work Together
Breast cancer provides one of the easiest examples of biomarker-guided treatment.
After breast cancer is diagnosed, tissue is commonly tested for estrogen receptor (ER), progesterone receptor (PR), and HER2. These results help define biological subtypes and guide treatment choices.
1. Hormone Receptors
When cancer cells express estrogen or progesterone receptors, hormones can contribute to tumor growth.
Hormone receptor-positive breast cancers may therefore respond to endocrine therapies that reduce hormone production or interfere with hormone signaling. Tumors lacking those receptors are unlikely to benefit from treatments whose purpose is to block that pathway.
2. HER2
HER2 is a growth-related protein found at increased levels in some breast cancers.
Determining HER2 status helps identify patients whose tumors may respond to HER2-directed therapies. The same general principle applies across targeted oncology: find the molecular dependency, then determine whether a drug can exploit it.
One biopsy can therefore provide information not only about what cancer is present but also about which biological pathway may be therapeutically useful.
Biomarkers Can Guide Immunotherapy
Targeted therapy is not the only area where biomarkers matter.
Modern cancer treatment also includes immunotherapy, which attempts to help the immune system recognize or attack malignant cells more effectively.
Biomarker testing can help determine whether some immunotherapies are appropriate. NCI specifically notes that certain targeted treatments and immunotherapies work only, or work better, in cancers with particular biomarker patterns.
Depending on tumor type and treatment context, testing may evaluate immune-related proteins or genomic characteristics that reflect how cancer interacts with the immune system.
The important point for medical learners is that the biomarker may not always represent a molecule directly driving tumor growth.
Sometimes it reflects the relationship between the tumor and its immune environment.
This expands precision medicine from “Which mutation is driving the cancer?” to another question:
“What biological feature predicts that the patient’s immune system could respond to this therapy?”
Companion Diagnostics Connect a Test to a Drug
Some biomarker tests have an especially close relationship with treatment.
These are called companion diagnostics.
A companion diagnostic is designed to provide information that is important for the safe or effective use of a corresponding therapeutic product. FDA maintains a list of authorized companion diagnostic devices paired with specific oncology therapies or groups of therapies.
For example, FDA-authorized tests can identify EGFR mutations, ALK rearrangements, BRAF alterations, and other molecular abnormalities associated with particular targeted treatments in selected cancers.
This demonstrates how much the role of the pathology laboratory has changed.
The pathologist is no longer only answering:
“What cancer is this?”
Modern molecular pathology may also answer:
“Which treatment could this cancer be biologically vulnerable to?”
Liquid Biopsy Can Detect Tumor Material in Blood
Not every biomarker test requires a new tissue biopsy.
Cancer cells can release DNA and other biological material into the bloodstream. Tests designed to analyze this tumor-derived material are often called liquid biopsies.
NCI notes that biomarkers can be measured in tumor tissue but may also be detected in blood when tumors release cells or biological material into circulation.
This can be especially useful when obtaining tissue is difficult or when clinicians want molecular information without another invasive procedure.
FDA-authorized blood-based companion diagnostics already exist for several actionable biomarkers. For example, some plasma tests can detect specific EGFR alterations in non-small cell lung cancer and help identify patients for associated targeted therapies.
Liquid biopsy also has potential applications in monitoring tumor evolution because the molecular profile of cancer can change during treatment.
However, blood testing does not automatically replace tissue pathology. The appropriate sample and testing strategy depend on the cancer, clinical question, and limitations of the assay.
Biomarkers Can Help Monitor Treatment and Recurrence
Some tumor markers are useful after treatment has started.
When a measurable marker closely reflects tumor burden, repeated testing may help clinicians determine whether the cancer is responding.
A marker that falls during effective therapy may support evidence of response, while a later increase can sometimes raise concern about progression or recurrence.
The key word is sometimes.
Tumor markers should rarely be interpreted without context. Imaging, symptoms, physical examination, pathology findings, and other laboratory results may all contribute to understanding what a change means.
This prevents a common misconception:
A biomarker is usually evidence, not the entire diagnosis.
NCI emphasizes that elevated tumor markers alone generally cannot establish cancer because benign conditions can also raise some markers, and not every patient with a particular cancer will have an elevated associated marker.
Biomarkers Have Important Limitations
Precision medicine sounds simple when described as “find the mutation and give the matching drug,” but reality is more complicated.
A tumor may not contain an actionable biomarker. A detected alteration may not have an approved therapy for that clinical situation. Even when a target and drug are available, not every patient responds because cancers contain additional biological differences.
NCI notes that even cancers of the same type can have different biomarker patterns and that these differences can influence treatment response.
Tumors can also be heterogeneous, meaning different parts of the same cancer may contain different cell populations.
Biomarker status may even change over time. For example, NCI notes that hormone receptor status in breast cancer can change, which is one reason repeat testing may sometimes be useful when disease recurs.
Sample quality matters too.
The pathology laboratory must ensure that enough representative tumor is available and that the chosen testing method is appropriate. Molecular testing is therefore always part of a broader diagnostic process rather than a standalone answer.
A Simple Way to Understand Cancer Biomarkers
For medical learners, biomarkers become easier when grouped by the question they answer:
Diagnostic → What cancer is this?
Prognostic → How might it behave?
Predictive → Which treatment might work?
Monitoring → Is treatment working or has disease returned?
A single biomarker can sometimes provide information in more than one category.
The practical workflow often looks like this:
Biopsy → Morphologic diagnosis → Biomarker testing → Molecular classification → Treatment selection → Response monitoring
This is why pathology has become such an important part of precision oncology.
Modern cancer diagnosis increasingly combines what the tumor looks like with what the tumor expresses and what genetic changes it carries.
Cancer biomarkers guide diagnosis and treatment by revealing biological information that cannot always be seen from tumor size, location, or microscopic appearance alone.
Diagnostic markers help classify tumors, prognostic biomarkers provide clues about likely behavior, and predictive biomarkers can identify cancers that may respond to targeted therapy or immunotherapy.
Tests for markers such as hormone receptors, HER2, and EGFR show how molecular findings can directly influence treatment decisions.
Liquid biopsy and molecular profiling are adding even more ways to study cancer biology, but biomarkers still need to be interpreted alongside pathology, imaging, stage, and the clinical picture.
For medical learners, remember four questions: What is it? How will it behave? What might treat it? How is it responding? Those questions capture the practical value of cancer biomarkers.